Latin American Network · Model Center of Excellence 170 specialists · 14 countries

Homogenize the comprehensive treatment of endometriosis in Latin America.

Endometriosis is a systemic, inflammatory and neurofunctional diseasenot a "menstrual pain." EndoLATAM articulates centers, ambassadors and legislators so that every patient on the continent can access the same standard: expert endomapping, classification #ENZIAN, pain phenotyping, complete excision surgery and a team multidisciplinary that measures its results.

Is he patient? Make the 2-minute quick self-assessment and know what to ask your team →
> 200 M
patients affected by endometriosis in the world, most without diagnosis
Expert opinion on EndoLATAM 2026 · WHO: - 190 M (- 10%)
5 / 22
countries of the region with comprehensive national endometriosis law in place
EndoLATAM verification, oct 2026
7–10 years
in Mexico
Expert Opinion EndoLATAM 2026

The classic figure of "1 in 10" was born when the diagnosis required laparoscopy and biopsy. Today there is no Latin American study of its own which measures the actual incidence of the disease: the network intends to generate it.


The problemRegional fragmentation

A systemic disease treated by fragments.

In Latin America, patients have been passing through emergencies, general gynecology, gastroenterology and urology for years. Each consultation treats a symptom and none of them integrate the disease. The result is diagnostic delay, incomplete surgeries, Central awareness not recognized and reproductive decisions made with half the information. And the region still doesn't know how many patients have: the prevalence of 1 in 10 was estimated at the time the diagnosis was made by laparoscopy and biopsywith an expert image the real denominator is unknown and no study of Latin America He's measured it.

Comparison between the fragmented care route and the EndoLATAM homogenized route Start of symptoms 7-10 years later
Consultation / interventionDecision changing the prognosisNo diagnostic value

Average diagnostic delay (Mexico)
7-10 years
Expert Opinion EndoLATAM 2026
Patients with persistent pain after technically successful surgery when applied in isolation
up to 70%
Doyenne White Paper v1.2, 2025
Standard gynaecological ultrasound informed "normal" in deep endometriosis when the operator is not trained
≈70 %
Expert Opinion EndoLATAM 2026 (Sierra Brozón)
Countries in the region with comprehensive national endometriosis law in place
5 of 22
Legislative verification EndoLATAM, oct 2026
Population studies specific to Latin America on the actual incidence of endometriosis (figure 1 in 10 comes from series diagnosed by laparoscopy and biopsy)
0
EndoLATAM Network, 2026
Countries with national patient registration established by law (Colombia, Peru, Panama) and none with verified public results
3 of 22
Legislative verification EndoLATAM, oct 2026
Metric

Indicators that EndoLATAM measures to close the gap

< 12 months
Target of time to diagnosis from first contact with the system (today: 7-10 years in Mexico, Expert Opinion 2026)
100 %
Patients with endomapping and #ENZIAN documented prior to any surgery (today the standard ultrasound is "normal" in h70% of the deep disease)
T0 · T1 · T3
Mandatory admission PROMs, 3 and 12 months in all accession centers
1
Regional incidence cohort with expert image diagnosis (goal: first study of Latin America)

If your center already measures these indicators, it is part of the solution. If not yet, the network provides the instrument.

The modelCenter of excellence

Complete termination as standard. Equipment as a condition.

The EndoLATAM model is not a surgical technique: it is an architecture of attention. The complete excision of all affected compartments In a single surgical time it's the standard and around it we organize a team that phenotipates pain, protects function and measures results. The disease resolution and functional restoration they are the goal, the symptomatic management and the failure we are trying to eradicate. On the net No one operates alone: centers and specialists always work in multidisciplinary teams and are bound to publish your incidents, complications, PROMs and results.

Multidisciplinary Ring around the complete excision EXCISIONCOMPLETA+ patient at the center
Network position

Termination, never ablation.

The EndoLATAM network is against ablation (coagulation, vaporization or "burning" the lesions) as treatment of endometriosis. The ablation leaves disease under the surface, prevents histological confirmation and is associated with more recurrence and more reinterventions. No modern and serious group, no center of excellence, uses it. If a patient is offered ablation, the network's recommendation is to seek a second opinion in a center that practice complete excision with multidisciplinary equipment.

×4.1

Full and born alive. In 100 operated infertile patients, 50 achieved spontaneous conception and 40 a living child in the first year and complete excision increased by 4.1 (95% CI 1.1- 14.9) the probability of living birth. The authors recommend looking for an expert surgeon in excision techniques.

Nguyen et al., J Minim Invasive Gynecol 2025, 32: 718-724
OR 0.17

Excision against ablation of endometrioma. Less endometrioma recurrence (37% after ablation vs. 5-17% after excision), less re-interventions (OR 0.16, 32% vs 3-16%), less recurrence of dysmenorrhea (OR 0.25) and dispareunia (OR 0.09). Spontaneous pregnancy a year with clear difference (OR 1.27, low certainty).

Kalra et al., Cochrane Database Syst Rev 2024, CD004992

EndoLATAM standardized care route · 7 steps

1
Admission

Digital admission + PROMs T0

NRS, CSI, PCS, PHQ-9, GAD-7, EHP-30, FSFI, ICIQ-SF, GSRS, BPI before the first consultation.

2
Image

Endomapping RM + US expert

Map by compartments with complete #ENZIAN classification, including intestinal, urinary and nervous involvement.

3
Pain

Pain phenotyping

Nociceptive, neuropathic, nociplastic or mixed, pelvic floor assessment and central awareness.

4
Committee

Multidisciplinary Committee

It secates anatomical indication of temporary urgency and defines who operates and how and with what equipment.

5
Optimization

Comprehensive preparation

Neuromodulation, physiotherapy, mental health, nutrition and fertility strategy (AMH, preservation) before operating.

6
Surgery

Complete multi-organizational excision

A surgical time, all compartments, colorectal, urological and neuropelic equipment available.

7
Results

Rehabilitation and follow-up

PROMs T1 (3 m) and T3 (12 m), recurence, intestinal and urinary function, fertility, EndoLATAM registration.

Metric

Results to be published by a model center

EHP-30
Change in specific quality of life between T0 and T3 (target: clinically significant improvement in all domains)
OR 0.17
Retirement of endometrioma a year with an excision versus ablation (37% after ablation vs. 5-17% after excision) · Cochrane 2024
×4.1
Probability of live birth with complete excision in infertile patients (50% spontaneous conception and 40% live birth 12 months after surgery) · JMIG 2025
100 %
Claren-Dind Complications reported in open access (transparency as a certification criterion)

The complete protocols (admission, image, committee, surgery, follow-up) are available for the adhesion centers.

Mapping ProtocolEndomapping · #ENZIAN

Endomapping: the map before O.R. 's.

No deep endometriosis surgery begins without a complete map. The EndoLATAM protocol combines MRI with endometriosis protocol y expert transvaginal ultrasound (intestinal preparation, slide sign, rectal muscle assessment, ureters and kidneys) to describe each compartment with the classification #ENZIANincluding the commitment intestinal, urinary, nervous and extrapelvic. A "normal" ultrasound without this protocol does not rule out deep disease.

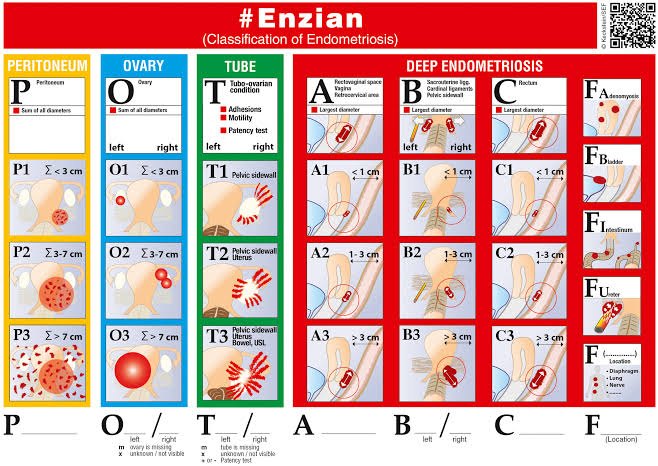
Classification poster #ENZIAN of endometriosis: compartments P (peritoneum), O (ovary), T (tube and tubo- ovarian adhesions), A (rectovinal and vagina septum), B (uterosacre and parametrium ligaments), C (rectum) and F (adenomyosis, bladder, intestine, ureter and other locations), with gradation 1 to 3 per size
Classification #ENZIAN (Keckstein et al., 2021): The common language of endomapping EndoLATAM. Peritoneum (P), ovary (O) and tuboo-ovary adhesions (T) are graded 1-3 by extension, rectovaginal vagina / septum (A), uterosacros / parametrio (B) and rectimer (C) by diameter (< 1 cm, 1-3 cm, > 3 cm) and F describes adenomyosis (FA), bladder (FB), intestine (FI), ureter (FU) and other locations. Left / right sides at O, T, B and FU. Image: © #ENZIAN · Stiftung Endometrioseforschung (SEF). Reproduced for educational purposes and confirm license of use prior to publication.
Teaching simulatorStandardized report

Build the #ENZIAN report of the endomapping

Select the extension by compartment (0 = absent, 1 < 1 cm, 2 = 1-3 cm, 3 > 3 cm for A, B and C and for P and O: 1 < 3 cm, 2 = 3-7 cm, 3 > 7 cm). Fates in order left / right. The resulting code is the common language that the network requires in all derivation.

#ENZIAN P0, O0/0, T0/0, A0, B0/0, C0

    Educational tool to standardize the language of the report. It does not replace the evaluation with an expert image or the decision of the multidisciplinary committee.

    Metric

    Mapping quality that the network has heard

    100 %
    RM and US reports with the 11 compartments #ENZIAN described explicitly (including "0" when free)
    ≥ 90 %
    Regional goal of concordance imagen- surgical finding per compartment, audited in each center
    100 %
    Renal and ureteral evaluation documented in any B or C compartment commitment
    0
    Scheduled surgery without prior endomapping in certified centers

    The acquisition protocol (MRI sequences, intestinal preparation for US, reporting template) is delivered to radiologists and ecographists of the network.

    Pain phenotypesThe phenotype defines the plan, not the image

    Three mechanisms, three plans different.

    The image says where the lesion is and the phenotype says why it hurts. The pain of endometriosis progresses with peripheral sensitization, central y nociplastic. Operating on a patient with a predominantly nociplastic pain phenotype without prior stabilization perpetuates pain; leaving deep nociceptive disease untreated can make pain chronic. That is why pain phenotyping (using validated instruments and assessment of the pelvic floor) is a mandatory step in the protocol.

    How the plan changes

    Admission profileT0 instruments

    Explore how the instruments guide the dominant phenotype

    Protocol operating thresholds: CSI ≥ 40 indicates moderate central sensitization (≥ 60 severe); PCS ≥ 20 indicates clinically significant pain catastrophizing; NRS ≥ 7 indicates severe pain. The sliders are educational: they illustrate the logic but do not replace clinical assessment.

    Intensity of pain
    Central Sensitization Inventory
    Pain catastrophizing
    Sciatic, pudendal, or obturator distribution; allodynia, burning, or nighttime symptoms
    Localized, cyclical, and responsive to NSAIDs or hormonal therapy

    Educational guidance based on thresholds of the EndoLATAM protocol. The therapeutic decision is taken by the multidisciplinary committee with the patient.

    Metric

    What phenotyping must change in results

    100 %
    Patients with documented pain phenotype before indicating surgery
    CSI
    Reduction in central sensitization from T0 to T3 in patients with a nociplastic phenotype treated multimodally (target: CSI < 40 at T3)
    0
    Reinterventions indicated with CSI ≥ 60 without prior stabilization
    100 %
    Patients with pelvic floor dysfunction who start physiotherapy prior to surgery (meta)

    The phenotyping algorithm and the instruments (CSI, PCS, EHP-30 and the rest of the T0 set) are part of the network protocol package.

    Laws on the protection of the patient22 countries · verification oct 2026

    A continent, 22 legal frameworks different.

    Alone five countries of the region have an existing comprehensive national endometriosis law: Panama (2021), Colombia (2023), Peru (2023), Paraguay (2024) y Uruguay (2024). The rest of the region relies on declarative laws, subnational rules, stalled bills, or no specific legislation. Each country profile links to its official source; anything that could not be verified is marked accordingly. A regional model law does not yet exist through PAHO or PARLATINO, so EndoLATAM proposes one.

    Map of Latin America with legislative light of endometriosis by country
    National comprehensive law in force Partial (declarative, subnational, coverage or half-sanction) Only projects in progress No identified legislation Unverified
    Regional comparison

    What each country guarantees today

    CountryNational lawTypeexplicit coverageLabour protectionPatient registrationNational DayTrust

    Source: EndoLATAM documentary review of official gazettes, legislative portals, and health ministries, current through October 5, 2026. “Explicit coverage” means a legal mandate or specific national technical standard; “Employment protection” means a rule recognizing accommodations, disability leave, or job protection related to endometriosis, not necessarily additional paid leave.

    EndoLATAM proposalRegional framework law · 7 pillars

    Regional framework law on comprehensive endometriosis care

    Built about what already works under the laws of Panama, Colombia, Peru, Uruguay and Paraguay and about what none still requires: standards of complete excision, certified centers and public results. A text put forward as revised by the network's legal committee and will be published on this platform at the end of consultation with patient associations.

    1

    Recognition as chronic, systemic and inflammatory disease

    With effects on coverage, disability and labour and educational protection.

    Reference: Panama Law 213 (art. 9) · Uruguay Decree 72 / 026
    2

    Timely diagnosis with expert image

    Sampling of every patient with chronic pelvic pain or infertility; endomapping (MRI + US expert) financed prior to any surgery.

    Reference: Peru Law 31868 (screening) · Innovation EndoLATAM (endomapping)
    3

    Compulsory comprehensive and multidisciplinary coverage

    Complete removal, colorectal and urological surgery, pain therapy, physiotherapy, mental health, nutrition and fertility in all public and private providers.

    Reference: Uruguay Law 20.374 + Decree 72 / 026 · Colombia Law 2338 (art. 6)
    4

    Certified reference centers

    Volume credit, equipment, endomapping, phenotyping and production of results and guaranteed referral of complex cases.

    References: Brazil PL 1069 / 2023 (regional centers) · Argentina Law 15491 PBA · Innovation EndoLATAM (certification)
    5

    National registration with PROMs and open data

    Registration of patients with complete phenothiping, #ENZIAN, recurrence, fertility and complications, published annually.

    Reference: Colombia Res. 2068 / 2025 (SISPRO) · Peru Law 31868 (MINSA registration)
    6

    Labour and educational protection

    Reasonable adjustments, recognition of disability, freedom from dismissal and justified absences in education.

    Reference: Colombia Law 2338 (art. 9) and Decision T-448 / 2023 · Panama Law 59 / 2005 · Uruguay Law 20.374
    7

    Training, awareness-raising and financing

    Compulsory undergraduate training and specialties, annual campaigns (14 March) and specific budget with impact assessment.

    Relatives: Colombia, Uruguay, El Salvador (14 March) · Brazil Lei 14.324 (13 March)
    Metric

    Legislative indicators that the network monitors

    5 / 22
    Countries with comprehensive national law in force (network target: 22 / 22)
    4
    Countries with published national technical standards or regulations (Colombia, Peru, Uruguay, Brazil-PCDT)
    3
    Countries with comprehensive project approved in a camera and detained (Brazil, Chile, Puerto Rico)
    9
    Countries without identified or unverified legislation: network impact priority

    Are you a legislator, an adviser or a patient association? The network provides the basic text, regional evidence and technical accompaniment.

    Network of members and centers170 specialists · 14 countries

    A network that CertificatesNot that he's just calling.

    EndoLATAM is a community of certified endometriosis specialists integrating gynecology and surgery with minimum invasion, image, colorectal surgery, urology, neuropelviology, anesthesia and pain, pelvic floor physiotherapy, mental health, nutrition and reproductive medicine. The board brings together its members by country and the centers are attested by measurable results: PROMs, recurrence, fertility, complications and time to diagnosis.

    @endolatam42.1 K followers · "Community of certified experts in Endometriosis of Latin America. Find your nearest specialist here!"
    Network centersReference sites and Master Surgeons SRC

    Where the network operates: headquarters, certified centers and attention points

    Two Baseline articulate the network: Doyenne Institute (Mexico City), with three designations SRC Master Surgeon verified in complex and multidisciplinary care of endometriosis, creator of the block technique for deep disease with intestinal involvement, affiliated to the International Society of Neuropelveology (ISON) and attested by the College of Disney Knowledge and ALGIA (Pereira, Colombia), advanced gynaecological laparoscopy unit and pelvic pain directed by Dr. Juan Diego Villegas- Echeverri. Around them, the centers where the members of the board attend. A non-negotiable rule: no center or network specialist works aloneand multidisciplinary equipmentand each center publish your incidents, complications, PROMs and results. Touch a point on the map to see the center, its credits (with source) and its equipment.

    You can also touch a country on the map to see its specialists. The results highlight the cities with known headquarters.

    Map of Latin America with the headquarters and centers of the EndoLATAM network
    Reference location (Doyenne · ALGIA) SRC Master Surgeon Designation verified Doyenne Institute High Headquarters Center / office of members

    Documentally verified locations and credits at 5-oct-2026 (public spots from Spring Review Corporation 2022-2026, official center sites, endolatam.org directory). Only centers with institution or town supported by source are shown and 43 members with no published institution do not appear on the map but do appear on the directory. CRS does not publish a consultative directory: an unannounced designation may be missing and information about its co-ordination.

    Source: endolatam.org Medical Directory (accessed October 5, 2026) and Instagram @endolatam. Photographs and contact details were published by the network; each member may request updates through regional coordination.

    Level 1

    Adhesive center

    • Adopts the 7-step route and report template #ENZIAN
    • Apply the set of PROMs in T0, T1 and T3 to all patients
    • Derives cases with intestinal, urinary or nervous involvement to a certified center
    • Publishes annually its casuistics, complications and PROMs and participates in registration and continuing training (compulsory at all levels)
    Level 2

    EndoLATAM certified center

    • Stable multidisciplinary equipment: expert image, colorectal surgery, urology, neuropelviology, pain, physiotherapy, mental health, nutrition and fertility
    • Annual volume of published and audited complete multiorganic excision surgeries, with colorectal and urological equipment in all cases of C, FB or FU compartment
    • Weekly multidisciplinary committee documented and phenotyped pain in 100% of cases
    • Annual publication of results and complications in open access and external audit of the network
    Level 3

    Regional reference center

    Today: Doyenne Institute (CDMX, SRC Master Surgeon × 3, creator of block technique, ISON, College of Disney Knowledge) and ALGIA (Pereira). Red-verified SRC Master Surgeon Designations: Dr. Ramiro Cabrera Carranco (2), Dr. Ana Gabriela Sierra Brozzo (1) and Dr. José D. Eugenio-Colón (5).

    • Receive complex cases from other countries and network fellows
    • Lidera lines of research of the EndoLATAM cohort (complete phenothiping + #ENZIAN + longitudinal monitoring)
    • Standard Lean-focused processes: road times, waiting lists and cost per episode published
    • Technically advises national legislative processes
    Scientific transparencyMultidisciplinary teams that publish

    Centers and specialists that measure and publish: incidents, complications, PROMs and results

    EndoLATAM certification is not declared, is demonstrated. Each center works in multidisciplinary equipment and publishes, with a verifiable academic identity, its Casualistic, complications, PROMs and their surgical and reproductive results. Examples of ORCID records of network surgeons:

    Recent joint publications of the network (PubMed)

    • V-NASE in bloc laparoscopy hysterectomy with segmental bowl resection for deep infiltrating endometriosis (#ENZIAN C3) · Facts, Views & Vision in ObGyn, 2026 · Burgos Gámez, Cabrera Carranco, Kondo, Diniz Osaki, Vigueras Smith, Eugenio- Colón, Vera Hernández · DOI 10.52054/FVVO.2026.300
    • Advanced emergency techniques in minimally invasive surgery: multidisciplinary approach for silent obstructive uropathy in deep endometriosis Eur J Obstet Gynecol Reprod Biol, 2026 Chaul, Cabrera Carranco, Menocal Tavernier, Kondo, Sierra Brozón, Vera Hernández DOI 10.1016 / j.ejogrb.2026.114963
    • Intestinal resection and redo anastomosis following anastomotic dehiscence post segmental bowl endometriosis surgery · J Minim Invasive Gynecol, 2025 · Fuentes, Maestri, Gressele, Kondo · DOI 10.1016/j.jmig.2025.06.009

    ORCID records verified at 6 -oct-2026 at orcid.org. Rejected publications from PubMed (6-oct-2026) are referred to as an example of co-production, but have been referred to as an exhaustive list.

    Form of accession

    Get on the net.

    Hospital centers, surgeons, radiologists and ecographists, physiotherapists, mental health and nutrition professionals, scientific societies, patient associations and legislative teams. When sending, the form generates a structured request that you can copy and send to regional coordination.

    Institutional contact

    Regional coordination EndoLATAM

    Email: contacto@endolatam.net

    Telephone: +52 55 5470 2598

    This mail and telephone are exclusively for professional administration and contact (centers, specialists, societies, legislators and the press). No care or guidance is provided to patients through this route: patients should contact the specialists of the directory directly.

    For reference to complex cases (intestinal, urinary, nervous or extrapelvic involvement), and prior incomplete surgeries, and severe notiplastic phenotype), indicate them at the request type.

    Mandatory fields.

    Capacities available in your institution
    Do not include identifiable clinical data from patients.
    Metric

    How the network is measured

    128
    Members of the regional directory (14 countries), with photo and specialty verified at endolatam.org
    6
    Reported SRC Master Surgeon appointments at network surgeons (3 surgeons) and target: at least 1 certified center per country
    T0 · T1 · T3
    EndoLATAM cohort: complete phenotipate, #ENZIAN and longitudinal monitoring and recruitment open to all stick centers
    12 months
    Recertification and audit cycle of results

    The network grows by certification, not by marketing: each center that enters is committed to measuring and publishing.

    Education and trainingHigh-performance equipment

    Training equipment, not just surgeons.

    Homogenization is built by training each link of the route with the same standard: who makes the image, who phenises pain, who operates, who rehabilitates and who measures. Programmes common curriculum, evaluation of skills and link to the EndoLATAM cohort. Dates, headquarters and quotas are published on this platform and in @endolatam with each call.

    Fellowship

    Multiorganic deep endometriosis surgery

    Surgical Immersion with complete excision with colourrectal, uropelic and uropelic equipment, committee, endomapping planning and monitoring of results.

    Headquarters: certified network centersDuration and quotas according to call
    Course

    Endomapping: RM and expert ultrasound

    Acquisition protocol, slide sign, rectal muscle assessment, ureters and kidneys, report template #ENZIAN and surgical correlation.

    Radiologists and ultrasoundOnline theory + practice in network centers
    Course

    Phenothipate of pain and neurophelviolology

    Peripherical, central and nociplastic sensitification; T0 instruments; pelvic neuropathic pain (cyatic, pounding, shutting) and criteria for indication and surgical deviation.

    MultidisciplinaryOnline theory + clinical cases
    Agenda

    Pelvic floor physiotherapy in endometriosis

    Evaluation of hypertonia and trigger points, presurgical preparation and functional rehabilitation (intestinal, urinary, sexual) integrated into the 7-step route.

    Physical therapistsOnline theory + supervised practice
    Module

    Mental and neuropsychiatric health

    Real biopsyco-social impact: PHQ-9 and GAD-7 with risk flags, catastrophication, trauma, sexuality and perioperative accompaniment.

    Psychiatry and psychologyBased on Expert Opinion 2026
    Workshop

    Personalized fertility in endometriosis

    Ovarian Reserve (AMH, AFC) interpreted in endometriomas, EFI-Plus, maintenance and surgical sequence -assisted reproduction; IVF isn't automatic.

    Reproductive medicineWith AMMR
    Expert opinion EndoLATAM · Punta Cana 2026Transdisciplinary treatment of chronic pelvic pain and fertility in endometriosis · AMMR / EndoLATAM
    Mexican Consensus of Endometriosis 2025EndoLATAM · operational definition as systemic neuroimmune disease
    Algortimo Vera / Cabrera 2025Anatomical indication vs. temporary surgical urgency integrated to the pain phenotype
    EFI-Plus 2025Endometriosis fertility index updated with AMH, adenomyosis and #ENZIAN · regional multicentre study
    Doyenne White Paper v1.2 (2025)Care architecture of the center of excellence and persistence of pain after isolated surgery
    External references of the protocol#ENZIAN (Keckstein et al., 2021) · FIGO-IPPS “R U MOVVING SOMe” (Lamvu, Villegas-Echeverri et al., 2025) · ESHRE 2022
    Metric

    Training measured by skills

    128
    Specialists from 14 countries already integrated into the network and its common curriculum (basis for continuing training)
    100 %
    Evictions applying the #ENZIAN template and the PROMs set in its center at 6 months (goal)
    ≥ 90 %
    Image consistency - surgery required for endomapping course graduates (target audited)
    1 / month
    Regional scientific session (complex cases and cohort results)

    The programmes are opened by call to the network centers and individual professionals.

    PatientsRights · what to demand · where to go

    What every patient has the right to demand.

    The pain that prevents working, studying or having sex is not normal and is not "part of being a woman." You are entitled to an expert image diagnosis, a complete plan and a team that measures if you are improving. This section translates the existing laws and the EndoLATAM standard into concrete actions.

    Fast self-evaluation · 2 minutes11 questions

    Should your team apply the full pain phenotype questionnaires?

    Answer these summary questions of the instruments used by the network (NRS, CSI, PCS, PHQ-9, GAD-7, EHP-30, FSFI, ICIQ-SF, GSRS). The result tells you if there is a alarm signal and what questionnaires and studies to ask your team or a network expert. It is not a diagnosis: it is the way to get to the consultation with the correct information.

    Your answers are not sent to any server: everything happens on your device.

    Current duties by country (verified)

    • 🇨🇴
      Colombia Law 2338 / 2023: flexible hours or remote work and recognition of disability, public policy 2025-2034 and patient registration.Constitutional Court, T-448 / 2023: endometriosis is a disabling condition.
    • 🇺🇾
      Uruguay Act No. 20374 and Decree No. 72 / 026: diagnosis and complete treatment of all providers with multidisciplinary equipment and reasonable work adjustments.Recognized as chronic and systemic inflammatory disease.
    • 🇵🇦
      Panama Act 213 / 2021: chronic disease and public form medicines and labour protection through Act 59 / 2005.First comprehensive law of the region.
    • 🇵🇪
      Peru Act 31868 / 2023 and NTS 236-2025: care for every patient with chronic pelvic pain or infertility, specialized units and national registration.Apply to SIS, EsHealth, EPS and private providers.
    • 🇵🇾
      Paraguay · Law 7341 / 2024: comprehensive treatment of endometriosis and adenomyosis and protection against dismissal due to pain-related absences.Exact scope to be verified in official text.
    • 🌎
      Rest of the region · See your country's file on the legislative map: provincial laws (Argentina), PCDT of SUS (Brazil), PAD FONASA (Chile), state licenses (Mexico) and ongoing projects.

    What to demand before any surgery

    0 of 7 criteria met

    How to find a center

    1

    Search the network by country.

    Use the membership directory and center map of this page: they are organized by country, with reference headquarters and verified credits.
    2

    Ask the 7 questions on the list.

    A center of excellence answers them all without being upset and if an answer is "no need," get a second opinion.
    3

    Take your previous studies.

    Previous surgeries (reports and video if any), images and hormonal treatments received.
    4

    If your case is complex, ask for reference.

    Intestinal, urinary or nervous commitment, incomplete surgeries or widespread severe pain require certified center.
    5

    Know your rights.

    If you live in a country with law, demand it. If you do, your patient association and network can accompany the legislative process.
    Metric

    Results that matter to the patient

    EHP-30
    Specific quality of life: the network reports improvement by domain, not just pain
    ×4.1
    More likely to be born alive with complete excision in infertile patients (JMIG 2025) and 50% conceive spontaneously in the first year
    < 30 days
    Target from first network consultation to full multidisciplinary plan
    1
    Surgery: the goal is to be the last

    If you are a patient or family member, check with the members directory by country and contact the specialist directly, and the institutional phone and mail of the network are for professional contact only. The network doesn't replace your treating equipment but helps them find the right one.